Stomach cancer pathophysiology
 From Wikidoc - Reading time: 12 min
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Fahad Hasan, M.D.[2] Omer Kamal, M.D.[3], Parminder Dhingra, M.D. [4], Mohammed Abdelwahed M.D[5]
|
Stomach cancer Microchapters |
|
Diagnosis |
|---|
|
Treatment |
|
Case Studies |
|
Stomach cancer pathophysiology On the Web |
|
American Roentgen Ray Society Images of Stomach cancer pathophysiology |
|
Risk calculators and risk factors for Stomach cancer pathophysiology |
Overview
[edit | edit source]Gastric adenocarcinoma develops through two biologically distinct pathways. The intestinal-type pathway is driven by inflammation and progresses stepwise through the Correa cascade. It is overwhelmingly initiated by Helicobacter pylori. The diffuse-type pathway is largely de novo and is centered on loss of E-cadherin (CDH1).[1][2][3] H. pylori is a WHO Group 1 carcinogen. Only about 1–3% of infected individuals develop cancer, which reflects the combined effect of bacterial virulence (particularly CagA), host genetics, and environmental cofactors.[1][4]
The 2014 The Cancer Genome Atlas (TCGA) classification sits on top of the Lauren histologic dichotomy. It defines four subtypes:
- Chromosomal instability (CIN)
- Microsatellite instability (MSI)
- Epstein-Barr virus–positive (EBV+)
- Genomically stable (GS)
These subtypes are independently prognostic and underpin the biomarkers that direct targeted therapy and immunotherapy: mismatch repair (MMR)/MSI, HER2, PD-L1, and EBV.[5][6][7]
About 10% of gastric cancers show familial aggregation, but only 1–3% are attributable to known germline variants. The most important of these is hereditary diffuse gastric cancer (HDGC), caused by germline CDH1 pathogenic variants. Contemporary penetrance estimates for HDGC are substantially lower than historical figures.[1][8][9]
Pathophysiology
[edit | edit source]General mechanism
[edit | edit source]- Gastric adenocarcinoma arises when chronic injury, infection, and accumulated genomic and epigenomic damage shift gastric epithelial cells toward:[1][10]
- Reduced apoptosis
- Increased proliferation
- Aberrant differentiation
- Helicobacter pylori is the dominant cause of gastric adenocarcinoma.
- Population-attributable risk is approximately 75% overall and approximately 89–90% for non-cardia cancer.[1][4][2]
- In a prospective Japanese cohort, gastric cancer developed in infected individuals but not in uninfected individuals.[11]
- A causal-inference analysis of 6.8 million Koreans estimated that H. pylori infection raised gastric cancer risk approximately 6-fold (RR 6.40, 95% CI 6.05–6.77).[12]
- Cofactors that amplify risk among infected individuals include:[13]
- More virulent strains
- Pro-inflammatory host genotypes
- High-salt or smoked diets
- Low iron levels
- Smoking
- Hypochlorhydria from parietal cell loss permits colonization by pro-inflammatory, genotoxic non-H. pylori gastric microbiota.[13][14]
Intestinal-type pathway (Correa cascade)
[edit | edit source]The Correa cascade describes the stepwise histologic progression of intestinal-type gastric carcinogenesis:[15][2]
Template:Family tree/summary= Correa cascade of intestinal-type gastric carcinogenesis| Normal gastric mucosa | |||||||||
| Chronic non-atrophic gastritis (H. pylori infection) | |||||||||
| Chronic atrophic gastritis (parietal cell loss, hypochlorhydria) | |||||||||
| Intestinal metaplasia | |||||||||
| Dysplasia (low → high grade) | |||||||||
| Invasive intestinal-type adenocarcinoma | |||||||||
- Progression risk:
- Annual progression from intestinal metaplasia to cancer is low, approximately 0.13–0.3% per year.
- Risk is highest with incomplete (type III) metaplasia and with extensive corpus involvement (antrum plus corpus).[2][16][17]
- CagA and the type IV secretion system:
- The cag pathogenicity island encodes a type IV secretion system that injects CagA into epithelial cells.
- CagA is phosphorylated at EPIYA motifs and binds SHP-2.
- It then aberrantly activates ERK–MAPK, Wnt/β-catenin, STAT3, and Hippo/YAP signaling.
- The result is increased proliferation, inhibition of apoptosis, invasion, and stem-cell expansion.[4][18][19]
- CagA-positive strains confer higher cancer risk than CagA-negative strains.[4][13]
- Inflammation and genotoxicity:
- VacA (notably s1/m1 genotypes), lipopolysaccharide, peptidoglycan, and neutrophil-activating protein amplify NF-κB-driven inflammation.
- This inflammation generates reactive oxygen and nitrogen species that cause DNA double-strand breaks and genomic instability.[4][20][21]
- Current evidence does not support nitric oxide alone as the principal mediator.
- Epigenetic field cancerization:
- H. pylori-induced inflammation upregulates DNA methyltransferases and activation-induced cytidine deaminase.
- This causes promoter hypermethylation and silencing of tumor-suppressor genes, including CDH1, CDKN2A/p16, and MLH1.
- Somatic TP53 mutations also accumulate.
- These field changes can persist after the organism is eradicated.[10][22]
- Driver mutations: TP53, KRAS, and APC/Wnt-pathway alterations accumulate as dysplasia emerges.[10][23]
- Refinement of the cascade: Single-cell and lineage-tracing studies add several cellular-level layers beneath the tissue-level sequence:[23][24][25]
- Spasmolytic polypeptide-expressing metaplasia (SPEM)
- Pyloric metaplasia
- Stem-cell plasticity
- Non-sequential and parallel trajectories
- Effect of eradication: Eradication of H. pylori reduces cancer incidence but has limited, if any, effect on established intestinal metaplasia.[17][26]
Diffuse-type pathway
[edit | edit source]- Initiating event: Loss of E-cadherin (CDH1) initiates diffuse-type cancer.
- Tumors are poorly cohesive.
- Intracytoplasmic mucin displaces the nucleus, producing signet-ring cells.
- Diffuse mural infiltration produces linitis plastica.[1][2][3]
- No defined precursor: Unlike intestinal-type disease, there is no well-defined precursor cascade. Tumors arise at a younger age and carry a worse prognosis.[1][27]
- Mechanism:
- E-cadherin is lost through somatic mutation, loss of heterozygosity, and promoter hypermethylation.
- Loss destabilizes adherens junctions and disrupts cell polarity and tension sensing.
- This enables epithelial–mesenchymal transition and single-cell invasion.[28][25]
- In murine models, E-cadherin loss in CD44+ gastric cells alone is sufficient to initiate multifocal signet-ring carcinoma. TP53 loss mainly accelerates progression.[28]
- Molecular correlate: Diffuse-type disease maps closely onto the TCGA genomically stable subtype, which is enriched for CDH1 and RHOA mutations and CLDN18–ARHGAP fusions.[5][29]
- Open question: Whether diffuse-type cancer is purely de novo, or shares early injury and field effects with the intestinal pathway, remains unresolved.[25][3]
Epstein–Barr virus–associated gastric cancer
[edit | edit source]- Burden: EBV is present in approximately 8–10% of gastric cancers worldwide, which is the largest absolute burden of any EBV-associated malignancy.[30]
- Clonality: Tumor cells carry a monoclonal EBV genome, which implies transformation from a single infected cell.[30][31]
- Mechanism:
- Latent viral products (EBNA1, LMP2A, EBERs, and BART miRNAs) drive DNA methyltransferase upregulation.
- This produces an extreme CpG-island methylator phenotype (CIMP) that silences tumor-suppressor genes.
- PIK3CA mutations and PD-L1/PD-L2 (CD274/PDCD1LG2) amplification are characteristic.
- TP53 is usually wild-type.[5][31][32][14]
- Phenotype: EBV+ tumors are typically:[31][32][33]
- Proximal in location
- More common in men
- Poorly differentiated with dense lymphoid stroma
- Associated with lower nodal metastasis
- Highly sensitive to immunotherapy
- Prognosis: Most data favor a better prognosis, but at least one analysis found no significant survival effect.[33][34]
Molecular Classification
[edit | edit source]Molecular subtype reflects tumor biology better than histology or anatomic location.[5][6][35] In a Memorial Sloan Kettering cohort of 1,438 patients, TCGA subtype was independently associated with cancer-specific survival after adjustment for stage and grade. Subtype was also more influential than tumor location in predicting treatment response.[7]
| Subtype | Approximate frequency | Key molecular features | Clinical and therapeutic relevance |
|---|---|---|---|
| Chromosomal instability (CIN) | ~50% | Aneuploidy, TP53 mutation, receptor tyrosine kinase–RAS amplifications (ERBB2/HER2, EGFR, FGFR2, KRAS), VEGFA | Most common subtype; enriched at the gastroesophageal junction and cardia and in Lauren intestinal-type tumors; HER2 amplification directs trastuzumab-based therapy, and VEGFR2 biology underlies ramucirumab[5][35][36] |
| Microsatellite instability (MSI) | ~20–22% | Mismatch repair deficiency (often MLH1 promoter hypermethylation); high tumor mutational burden | Older patients, female predominance, antral location; favorable prognosis; high response to PD-1/PD-L1 immune checkpoint inhibitors[5][6][37] |
| EBV-positive | ~9–10% | Extreme CpG-island hypermethylation; PIK3CA, ARID1A, and BCOR mutations; PD-L1/PD-L2 and JAK2 amplification; dense lymphoid stroma | Proximal stomach, younger men; marked immune infiltration; immunotherapy-responsive[5][31][14] |
| Genomically stable (GS) | ~20% | CDH1 and RHOA mutations, CLDN18–ARHGAP fusions, epithelial–mesenchymal transition features | Diffuse histology, younger patients; tendency toward peritoneal metastasis; poorer prognosis[5][29][38] |
- Anatomic distribution: GS and EBV+ tumors favor the proximal stomach, CIN concentrates at the gastroesophageal junction and cardia, and MSI favors the antrum.[6][36]
- ACRG classification: The Asian Cancer Research Group (ACRG) scheme defines four subtypes and overlaps substantially with TCGA:[8][39][38]
- MSI
- MSS/EMT (mesenchymal-like)
- MSS/TP53-active
- MSS/TP53-inactive
- The distinctive ACRG contribution is the MSS/EMT subtype. It is characterized by CDH1 loss, CLDN18–ARHGAP fusions, strong peritoneal-metastasis propensity, and the worst prognosis.
- Limitations in routine practice: TCGA and ACRG subtypes are not yet routine treatment determinants.
Genetics and Hereditary Syndromes
[edit | edit source]Hereditary gastric cancer syndromes
[edit | edit source]| Syndrome | Gene(s) | Key features |
|---|---|---|
| Hereditary diffuse gastric cancer (HDGC) | CDH1 (germline pathogenic variants in ~20–40% of clinically defined families); CTNNA1 (~2%) | Autosomal dominant; diffuse-type gastric cancer and lobular breast cancer; see below[28][8] |
| Gastric adenocarcinoma and proximal polyposis of the stomach (GAPPS) | APC promoter 1B point variants | Autosomal dominant fundic gland polyposis restricted to the proximal stomach[8] |
| Familial intestinal gastric cancer (FIGC) | Not defined | Intestinal-type cancers aggregating in families without gastric polyposis[1] |
| Lynch syndrome | MLH1, MSH2, MSH6, PMS2 | Elevated gastric cancer risk with MMR-deficient tumors[8] |
| Familial adenomatous polyposis | APC | Elevated gastric cancer risk[8] |
| Other syndromes | TP53 (Li-Fraumeni syndrome), STK11 (Peutz-Jeghers syndrome), BMPR1A/SMAD4 (juvenile polyposis syndrome), PTEN (Cowden syndrome), hereditary breast and ovarian cancer genes | Elevated gastric cancer risk[8] |
Hereditary diffuse gastric cancer
[edit | edit source]- Second hit: Neoplastic transformation requires somatic inactivation of the second CDH1 allele.[28]
- Occult intramucosal foci:
- Penetrance has been revised downward:
- Historical estimates from high-risk kindreds were approximately 70% in men and 56% in women.[41]
- NCCN-endorsed cumulative risks through age 80 are approximately 37–42% in men and 25–33% in women.[40]
- In a North American cohort of families with CDH1 variants, lifetime cumulative risk of advanced gastric cancer was 10.3% in male carriers and 6.5% in female carriers.[9]
- Risk is substantially higher with a strong family history; the estimate was 38% with 3 or more affected first-degree relatives.[9]
- Breast cancer risk: Female carriers have an approximately 37–55% lifetime risk of lobular breast cancer, which requires separate surveillance.[9][42]
- In a genotype-first European multicenter study, CDH1 pathogenic and likely pathogenic variants were positively associated with diffuse gastric cancer and lobular breast cancer.
- No such association was found for missense variants of uncertain significance.[43]
- Surveillance limitations and surgery:
- Surveillance endoscopy has limited sensitivity for multifocal superficial signet-ring foci and usually cannot distinguish pT1a from pT1b disease.
- Carriers are therefore offered risk-reducing total gastrectomy, typically between ages 20 and 30.
- Surveillance is reserved for carriers who defer surgery.[27][40][44][45]
- Decision-making: No genotype–phenotype predictor exists, and risk varies widely between families. Surgery-versus-surveillance decisions are therefore increasingly individualized.[9][40]
Gross and Microscopic Pathology
[edit | edit source]- Lauren classification:[1][3][22]
- Intestinal type: Gland-forming tumors arising on a background of atrophy and intestinal metaplasia. They are associated with H. pylori and occur predominantly in older men.
- Diffuse type: Poorly cohesive, often signet-ring cells infiltrating singly. Extensive mural infiltration produces a rigid, thickened stomach wall (linitis plastica).
- Combined use: The Lauren classification combined with molecular subtyping, rather than exhaustive histologic typing schemes, is what currently informs trials and management.[1][39]
-
 Diffuse-type gastric adenocarcinoma producing linitis plastica (diffuse mural thickening). Case courtesy of Dr Andrew Ryan, Radiopaedia.org, rID: 16159
-
 Poorly differentiated gastric adenocarcinoma (H&E, 400×). Public Domain, https://commons.wikimedia.org/w/index.php?curid=182915
-
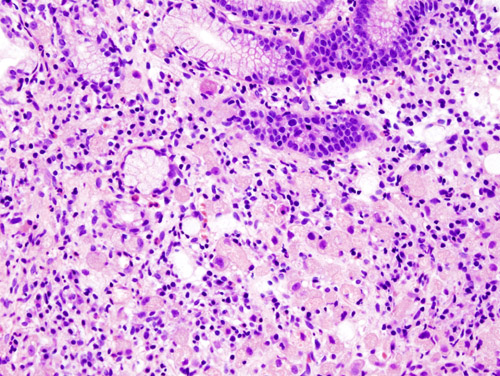 Signet-ring cell carcinoma: intracytoplasmic mucin displaces the nucleus to the cell periphery. CC BY-SA 3.0, https://commons.wikimedia.org/w/index.php?curid=502927


Clinical Correlations
[edit | edit source]- Test and treat H. pylori: Testing and eradication are indicated in patients with gastric neoplasia, premalignant lesions, or a family history of gastric cancer.
- High-risk premalignant mucosa: The following features identify mucosa at highest risk:[2][17]
- Extensive (antrum plus corpus) atrophy or intestinal metaplasia
- Incomplete intestinal metaplasia
- Persistent H. pylori infection
- Age older than 50
- Family history of gastric cancer
- Biomarker testing: Testing of gastric adenocarcinoma for MMR/MSI, HER2, PD-L1, and EBV follows directly from subtype biology.[6][8][7]
- MSI-high and EBV+ tumors predict checkpoint-inhibitor benefit.
- HER2 amplification (CIN subtype) directs trastuzumab-based therapy.
- Suspected HDGC: Patients should be referred to expert centers for CDH1/CTNNA1 testing and genetic counseling.[40][27]
Areas of Uncertainty
[edit | edit source]- Role of intestinal metaplasia: Whether metaplasia is an independent "point of no return" or a bystander is debated, as is which subset progresses. Chromosomal-instability features within metaplasia may identify progressors.[16][17][23]
- Natural history in CDH1 carriers: The progression rate from pT1a foci to advanced cancer, and the optimal timing of gastrectomy versus surveillance, remain uncertain.[9][40]
- Prognostic weight of EBV: The independent prognostic weight of EBV positivity is unsettled.[33][34]
- Origin of diffuse-type cancer: Whether it is purely de novo or shares an early field effect with the intestinal pathway is not established.[25]
References
[edit | edit source]- ↑ 1.00 1.01 1.02 1.03 1.04 1.05 1.06 1.07 1.08 1.09 1.10 1.11 Sundar R, Nakayama I, Markar SR, et al. (2025). "Gastric cancer". Lancet. 405 (10494): 2087–2102. doi:10.1016/S0140-6736(25)00052-2.
- ↑ 2.0 2.1 2.2 2.3 2.4 2.5 Gawron AJ, Shah SC, Altayar O, Davitkov P, Morgan D, Turner K, Mustafa RA (2020). "AGA Technical Review on Gastric Intestinal Metaplasia—Natural History and Clinical Outcomes". Gastroenterology. 158 (3): 705–731.e5. doi:10.1053/j.gastro.2019.12.001. PMID 31816300.
- ↑ 3.0 3.1 3.2 3.3 Bessède E, Dubus P, Mégraud F, Varon C (2015). "Helicobacter pylori infection and stem cells at the origin of gastric cancer". Oncogene. 34 (20): 2547–55. doi:10.1038/onc.2014.187.
- ↑ 4.0 4.1 4.2 4.3 4.4 Duan Y, Xu Y, Dou Y, Xu D (2025). "Helicobacter pylori and gastric cancer: mechanisms and new perspectives". J Hematol Oncol. 18 (1): 10. doi:10.1186/s13045-024-01654-2.
- ↑ 5.0 5.1 5.2 5.3 5.4 5.5 5.6 5.7 Cancer Genome Atlas Research Network (2014). "Comprehensive molecular characterization of gastric adenocarcinoma". Nature. 513 (7517): 202–9. doi:10.1038/nature13480. PMC 4170219. PMID 25079317.
- ↑ 6.0 6.1 6.2 6.3 6.4 Patel AK, Sethi NS, Park H (2026). "Gastric cancer: a review". JAMA. 335 (5): 439–450. doi:10.1001/jama.2025.20034.
- ↑ 7.0 7.1 7.2 Walch HS, Borpatragohain R, Jee J, et al. (2025). "Clinical implications of The Cancer Genome Atlas molecular classification system in esophagogastric cancer". Clin Cancer Res. 31 (10): 1912–1921. doi:10.1158/1078-0432.CCR-24-3473. PMID 40299774 Check
|pmid=value (help). - ↑ 8.0 8.1 8.2 8.3 8.4 8.5 8.6 8.7 8.8 Smyth EC, Nilsson M, Grabsch HI, van Grieken NC, Lordick F (2020). "Gastric cancer". Lancet. 396 (10251): 635–648. doi:10.1016/S0140-6736(20)31288-5.
- ↑ 9.0 9.1 9.2 9.3 9.4 9.5 Ryan CE, Fasaye GA, Gallanis AF, et al. (2024). "Germline CDH1 variants and lifetime cancer risk". JAMA. 332 (9): 722–729. doi:10.1001/jama.2024.10852.
- ↑ 10.0 10.1 10.2 Baba H, Ishimoto T, Baba Y, Hayashi H, Iwatsuki M (2026). "Advances in gastric cancer research: insights into carcinogenesis, the tumor microenvironment, metastasis, and factors influencing prognosis". Ann Gastroenterol Surg. 10 (4): 984–994. doi:10.1002/ags3.70195.
- ↑ Uemura N, Okamoto S, Yamamoto S, et al. (2001). "Helicobacter pylori infection and the development of gastric cancer". N Engl J Med. 345 (11): 784–9. doi:10.1056/NEJMoa001999. PMID 11556297.
- ↑ Oh HJ, Kim CH, Park HW, Park B (2025). "Quantifying the effects of the Correa pathway from Helicobacter pylori infection to gastric cancer: causal inference found in 6.8 million Koreans". BMC Cancer. 26 (1): 174. doi:10.1186/s12885-025-15507-9.
- ↑ 13.0 13.1 13.2 Malfertheiner P, Camargo MC, El-Omar E, et al. (2023). "Helicobacter pylori infection". Nat Rev Dis Primers. 9 (1): 19. doi:10.1038/s41572-023-00431-8.
- ↑ 14.0 14.1 14.2 Wizenty J, Sigal M (2025). "Helicobacter pylori, microbiota and gastric cancer — principles of microorganism-driven carcinogenesis". Nat Rev Gastroenterol Hepatol. 22 (5): 296–313. doi:10.1038/s41575-025-01042-2.
- ↑ Correa P (1988). "A human model of gastric carcinogenesis". Cancer Res. 48 (13): 3554–60. PMID 3288329.
- ↑ 16.0 16.1 Yeoh KG, Tan P (2022). "Mapping the genomic diaspora of gastric cancer". Nat Rev Cancer. 22 (2): 71–84. doi:10.1038/s41568-021-00412-7.
- ↑ 17.0 17.1 17.2 17.3 17.4 Sugano K, Moss SF, Kuipers EJ (2023). "Gastric intestinal metaplasia: real culprit or innocent bystander as a precancerous condition for gastric cancer?". Gastroenterology. 165 (6): 1352–1366.e1. doi:10.1053/j.gastro.2023.08.028.
- ↑ Hatakeyama M (2004). "Oncogenic mechanisms of the Helicobacter pylori CagA protein". Nat Rev Cancer. 4 (9): 688–94. doi:10.1038/nrc1433. PMID 15343275.
- ↑ Wan C, Wang P, Xu Y, et al. (2025). "Mechanism and role of H. pylori CagA-induced NLRP3 inflammasome in gastric cancer immune cell infiltration". Sci Rep. 15 (1): 14335. doi:10.1038/s41598-025-98301-8.
- ↑ El Tekle G, Garrett WS (2023). "Bacteria in cancer initiation, promotion and progression". Nat Rev Cancer. 23 (9): 600–618. doi:10.1038/s41568-023-00594-2.
- ↑ Müller A, He J (2023). "A double whammy on gastric cancer risk". N Engl J Med. 388 (13): 1225–1229. doi:10.1056/NEJMe2215503.
- ↑ 22.0 22.1 Ajani JA, Lee J, Sano T, et al. (2017). "Gastric adenocarcinoma". Nat Rev Dis Primers. 3: 17036. doi:10.1038/nrdp.2017.36.
- ↑ 23.0 23.1 23.2 Zhang T, Wang Z, Zhang B, Tang X (2026). "Refining the Correa cascade: gastric stem cell plasticity, niche remodelling, and parallel pathways to neoplasia". Pharmacol Res. 230: 108315. doi:10.1016/j.phrs.2026.108315.
- ↑ Cornish SK, Choi E, Mills JC, Goldenring JR (2026). "The origins and progression of pyloric metaplasia following gastric mucosal injury". Physiol Rev. 106 (4): 2441–2471. doi:10.1152/physrev.00042.2025.
- ↑ 25.0 25.1 25.2 25.3 Chen X, Wang S, Li J (2026). "Reframing early gastric carcinogenesis through lineage, niche, and evolution". Cancer Metastasis Rev. 45 (3): 67. doi:10.1007/s10555-026-10376-5.
- ↑ Kapteijn N, Marijnissen FE, Pluimers J, et al. (2026). "Dietary factors associated with the progression of gastric intestinal metaplasia: a multicenter, prospective cohort study in a Western population". Clin Transl Gastroenterol. 17 (5): e01006. doi:10.14309/ctg.0000000000001006. Vancouver style error: initials (help)
- ↑ 27.0 27.1 27.2 Vos EL, Salo-Mullen EE, Tang LH, et al. (2020). "Indications for total gastrectomy in CDH1 mutation carriers and outcomes of risk-reducing minimally invasive and open gastrectomies". JAMA Surg. 155 (11): 1050–1057. doi:10.1001/jamasurg.2020.3356.
- ↑ 28.0 28.1 28.2 28.3 28.4 Decourtye-Espiard L, Guilford P (2023). "Hereditary diffuse gastric cancer". Gastroenterology. 164 (5): 719–735. doi:10.1053/j.gastro.2023.01.038.
- ↑ 29.0 29.1 29.2 Liabeuf D, Oshima M, Stange DE, Sigal M (2022). "Stem cells, Helicobacter pylori, and mutational landscape: utility of preclinical models to understand carcinogenesis and to direct management of gastric cancer". Gastroenterology. 162 (4): 1067–1087. doi:10.1053/j.gastro.2021.12.252.
- ↑ 30.0 30.1 Hirabayashi M, Georges D, Clifford GM, de Martel C (2023). "Estimating the global burden of Epstein-Barr virus-associated gastric cancer: a systematic review and meta-analysis". Clin Gastroenterol Hepatol. 21 (4): 922–930.e21. doi:10.1016/j.cgh.2022.07.042. PMID 35963539 Check
|pmid=value (help). - ↑ 31.0 31.1 31.2 31.3 Damania B, Kenney SC, Raab-Traub N (2022). "Epstein-Barr virus: biology and clinical disease". Cell. 185 (20): 3652–3670. doi:10.1016/j.cell.2022.08.026.
- ↑ 32.0 32.1 Yang J, Liu Z, Zeng B, Hu G, Gan R (2020). "Epstein-Barr virus-associated gastric cancer: a distinct subtype". Cancer Lett. 495: 191–199. doi:10.1016/j.canlet.2020.09.019.
- ↑ 33.0 33.1 33.2 Zhao Y, Zhang J, Cheng A, et al. (2020). "Gastric cancer: genome damaged by bugs". Oncogene. 39 (17): 3427–3442. doi:10.1038/s41388-020-1241-4. Vancouver style error: initials (help)
- ↑ 34.0 34.1 Ozawa H, Wang Y, Withers HG, et al. (2025). "MUC1-C auto-regulatory complex with EBNA1 is responsible for latent Epstein-Barr virus-associated gastric cancer progression". Oncogene. 44 (38): 3609–3624. doi:10.1038/s41388-025-03519-5.
- ↑ 35.0 35.1 Felismino TC, Coimbra F (2023). "Lessons in gastric adenocarcinoma from TCGA". Nat Rev Cancer. 23 (10): 655. doi:10.1038/s41568-023-00606-1. Vancouver style error: initials (help)
- ↑ 36.0 36.1 Nakamura Y, Kawazoe A, Lordick F, Janjigian YY, Shitara K (2021). "Biomarker-targeted therapies for advanced-stage gastric and gastro-oesophageal junction cancers: an emerging paradigm". Nat Rev Clin Oncol. 18 (8): 473–487. doi:10.1038/s41571-021-00492-2.
- ↑ Van Cutsem E, Sagaert X, Topal B, Haustermans K, Prenen H (2016). "Gastric cancer". Lancet. 388 (10060): 2654–2664. doi:10.1016/S0140-6736(16)30354-3.
- ↑ 38.0 38.1 Johnston FM, Beckman M (2019). "Updates on management of gastric cancer". Curr Oncol Rep. 21 (8): 67. doi:10.1007/s11912-019-0820-4.
- ↑ 39.0 39.1 Chen J, Zhang X, Zhao Y (2026). "Advances in the molecular subtyping of gastric cancer". World J Surg Oncol. 24 (1): 314. doi:10.1186/s12957-026-04437-w.
- ↑ 40.0 40.1 40.2 40.3 40.4 40.5 National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Genetic/Familial High-Risk Assessment: Colorectal, Endometrial, Esophageal, and Gastric. Version 1.2026 (updated June 16, 2026). https://www.nccn.org
- ↑ van der Post RS, Vogelaar IP, Manders P, et al. (2015). "Accuracy of hereditary diffuse gastric cancer testing criteria and outcomes in patients with a germline mutation in CDH1". Gastroenterology. 149 (4): 897–906.e19. doi:10.1053/j.gastro.2015.06.003. PMID 26072394.
- ↑ Corso G (2022). "Pleiotropic cancer manifestations of germline CDH1 mutations: risks and management". J Surg Oncol. 125 (8): 1326–1331. doi:10.1002/jso.26847.
- ↑ Garcia-Pelaez J, Barbosa-Matos R, Lobo S, et al. (2023). "Genotype-first approach to identify associations between CDH1 germline variants and cancer phenotypes: a multicentre study by the European Reference Network on Genetic Tumour Risk Syndromes". Lancet Oncol. 24 (1): 91–106. doi:10.1016/S1470-2045(22)00643-X. PMID 36436516 Check
|pmid=value (help). - ↑ Laszkowska M, Silver ER, Schrope B, et al. (2020). "Optimal timing of total gastrectomy to prevent diffuse gastric cancer in individuals with pathogenic variants in CDH1". Clin Gastroenterol Hepatol. 18 (4): 822–829.e4. doi:10.1016/j.cgh.2019.06.009.
- ↑ Hirata Y, Noorani A, Song S, Wang L, Ajani JA (2023). "Early stage gastric adenocarcinoma: clinical and molecular landscapes". Nat Rev Clin Oncol. 20 (7): 453–469. doi:10.1038/s41571-023-00767-w.
 EncycloReader
is supported by the
 KSF