Categories
Tuberculosis screening
 From Wikidoc - Reading time: 12 min
|
Tuberculosis Microchapters |
|
Diagnosis |
|---|
|
Treatment |
|
Drug-Susceptible and Drug-Resistant Tuberculosis(ATS 2025 Guidelines) |
|
Case Studies |
|
Tuberculosis screening On the Web |
|
American Roentgen Ray Society Images of Tuberculosis screening |
|
Risk calculators and risk factors for Tuberculosis screening |
Editor-In-Chief: C. Michael Gibson, M.S., M.D. [1]; Associate Editor(s)-in-Chief: Joseph Nasr, M.D.[2]; Mashal Awais, M.D.[3]; Alejandro Lemor, M.D. [4]; Marjan Khan M.B.B.S.[5]
Tuberculosis screening
[edit | edit source]Tuberculosis (TB) screening is the risk-based identification of asymptomatic persons who may have Mycobacterium tuberculosis infection and who would benefit from further evaluation and treatment of latent tuberculosis infection (LTBI). Screening is performed using either the Mantoux tuberculin skin test (TST) or an interferon-gamma release assay (IGRA). Neither TST nor IGRA distinguishes LTBI from active TB disease, and neither test should be used to monitor response to treatment.[1][2]
Screening should be targeted to persons at increased risk for TB infection or increased risk of progression from LTBI to active disease. Universal testing of low-risk populations is not recommended because the positive predictive value is poor when pretest probability is low, and false-positive results may lead to unnecessary radiography, follow-up testing, and treatment.[3][1]
Who should be screened
[edit | edit source]The United States Preventive Services Task Force recommends screening for LTBI in asymptomatic adults aged 18 years or older who are at increased risk for TB infection.[3] The CDC and specialty guidelines also recommend testing selected children, contacts, healthcare personnel, and immunocompromised persons based on exposure risk and risk of progression.[1][4]
| Population | Screening recommendation | Notes |
|---|---|---|
| Persons born in, or with prolonged travel to, countries with high TB incidence | Screen for LTBI | Includes many countries in Africa, Asia, Eastern Europe, Latin America, and the Pacific Islands.[3][4] |
| Close contacts of persons with infectious TB disease | Screen and evaluate for active disease | Contact investigation may require repeat testing 8-10 weeks after last exposure if the initial test is negative.[1] |
| Current or former residents of congregate settings | Screen when exposure risk is increased | Includes homeless shelters, correctional facilities, long-term care facilities, and other high-risk congregate settings.[3] |
| Healthcare personnel | Baseline screening at hire or preplacement | Routine serial testing is not recommended unless exposure or ongoing transmission occurs.[5] |
| Persons with HIV infection | Screen at diagnosis regardless of epidemiologic risk | Repeat testing is recommended if initial testing is negative during advanced immunosuppression and immune reconstitution later occurs.[6] |
| Persons receiving or preparing for major immunosuppression | Screen before therapy when feasible | Includes tumor necrosis factor inhibitors, organ transplantation, and prolonged systemic glucocorticoids equivalent to prednisone ≥15 mg/day for ≥1 month.[1] |
| Persons with conditions increasing progression risk | Screen when epidemiologic risk or clinical context supports testing | Includes silicosis, hematologic malignancy, dialysis, and other immunosuppressive conditions.[2] |
| Low-risk asymptomatic persons | Do not routinely screen | If testing is mandated and the first test is positive, confirmatory testing is recommended before labeling the person infected.[1] |
Conditions such as diabetes mellitus, chronic kidney disease, low body weight, smoking, gastrectomy, and head or neck cancer increase risk of progression once infection is present, but they are not usually independent indications for LTBI testing without epidemiologic exposure risk.[2]
Screening algorithm
[edit | edit source]| Asymptomatic person considered for TB screening | |||||||||||||||||
| Assess epidemiologic risk, exposure history, immune status, and risk of progression | |||||||||||||||||
| Increased risk for TB infection or progression? | |||||||||||||||||
| Yes | No | ||||||||||||||||
| Perform IGRA or TST based on age, BCG status, return likelihood, and local availability | Do not routinely test unless mandated | ||||||||||||||||
| If positive: symptom screen and chest radiograph to exclude active TB disease | If tested despite low risk and positive: obtain confirmatory second test | ||||||||||||||||
| If active disease excluded: diagnose LTBI and offer treatment | Consider infected only if both tests are positive | ||||||||||||||||
Screening tests
[edit | edit source]Two test categories are used for LTBI screening: the TST and IGRAs. Both detect immune sensitization to M. tuberculosis antigens. Neither test can determine whether infection is latent or active.[1][2]
Tuberculin skin test
[edit | edit source]The Mantoux tuberculin skin test is performed by intradermal injection of 0.1 mL of purified protein derivative (PPD; 5 tuberculin units) into the volar surface of the forearm. A properly placed test produces a 6-10 mm wheal. The result is read 48-72 hours later by measuring the transverse diameter of induration, not erythema, in millimeters.[1][7]
The only absolute contraindication to TST is a prior severe reaction, such as necrosis, blistering, ulceration, or anaphylaxis, after a previous TST. TST is not contraindicated in pregnancy, infants, children, persons with HIV infection, or persons who received BCG vaccine.[7]
-
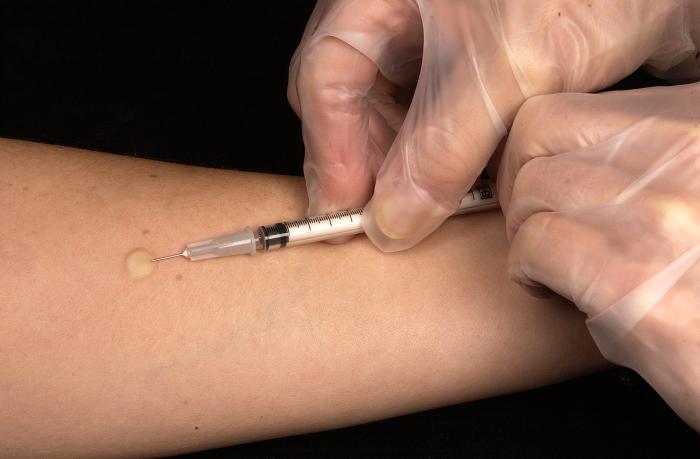 Mantoux tuberculin skin test placement. Image from the CDC Public Health Image Library.
-
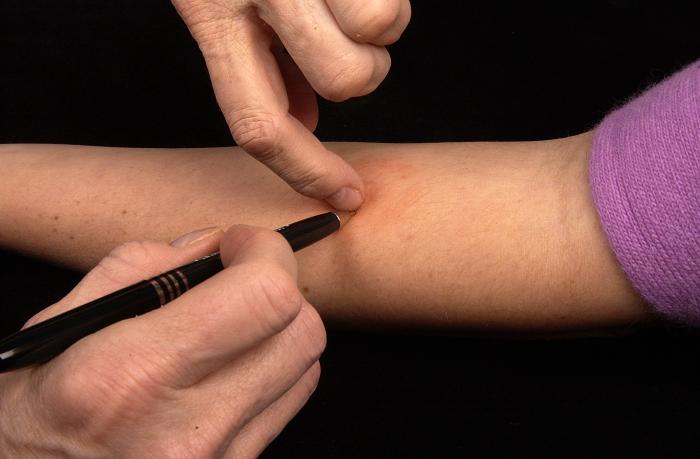 Tuberculin skin test reading. Image from the CDC Public Health Image Library.
-
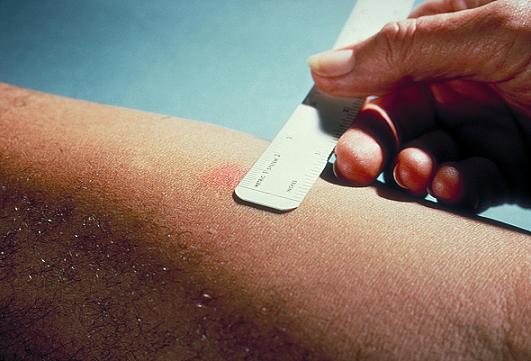 Tuberculin skin test reaction. Image from the CDC Public Health Image Library.


TST interpretation
[edit | edit source]TST interpretation depends on both the measured induration and the patient's risk of TB infection or progression to active disease.[1][7]
| Induration threshold | Considered positive in |
|---|---|
| ≥5 mm | Persons with HIV infection; recent contacts of infectious TB cases; persons with fibrotic changes on chest radiograph consistent with prior TB; organ transplant recipients; and other significantly immunosuppressed persons, including those receiving TNF-alpha antagonists or prednisone ≥15 mg/day for ≥1 month. |
| ≥10 mm | Persons born in or recently arriving from high-incidence countries; injection drug users; residents or employees of high-risk congregate settings; mycobacteriology laboratory personnel; persons with selected medical conditions that increase risk of progression; children younger than 4 years; and children or adolescents exposed to adults in high-risk categories. |
| ≥15 mm | Persons with no known risk factors for TB. |
Interferon-gamma release assays
[edit | edit source]Interferon-gamma release assays measure interferon-gamma release by T cells after stimulation with M. tuberculosis-specific antigens, including ESAT-6 and CFP-10. These antigens are absent from BCG strains and most nontuberculous mycobacteria, giving IGRAs higher specificity than TST in BCG-vaccinated persons.[1][2]
Two FDA-approved IGRAs are used in the United States:
| Test | Method | Positive threshold | Practical notes |
|---|---|---|---|
| QuantiFERON-TB Gold Plus | Whole-blood enzyme-linked immunosorbent assay measuring interferon-gamma response to TB-specific antigens | ≥0.35 IU/mL after subtracting nil control | Current-generation QuantiFERON assay; replaces older QFT-GIT in most settings.[8] |
| T-SPOT.TB | Enzyme-linked immunospot assay using separated peripheral blood mononuclear cells | ≥8 spot-forming cells | May be useful in selected immunocompromised patients; requires specialized processing. |
The 2023 USPSTF evidence review reported sensitivity of 89% for QuantiFERON-TB Gold Plus (95% CI, 84%-94%) and 90% for T-SPOT.TB (95% CI, 87%-92%). Reported specificity was 98% for QuantiFERON-TB Gold Plus (95% CI, 95%-99%) based on one study, and approximately 95%-97% for T-SPOT.TB based on two studies.[9] Indeterminate or invalid IGRA results occur in a minority of tests and should prompt repeat testing or use of an alternate test, depending on clinical context.[1]
Choosing between TST and IGRA
[edit | edit source]The choice between TST and IGRA depends on age, BCG vaccination history, likelihood of return for TST reading, immune status, test availability, and local practice.[1]
| Clinical context | Preferred test | Rationale |
|---|---|---|
| Age ≥5 years with history of BCG vaccination | IGRA preferred | Higher specificity because IGRA antigens are absent from BCG.[1] |
| Age ≥5 years and unlikely to return for TST reading | IGRA preferred | Requires only one encounter. |
| Other persons ≥5 years who meet criteria for LTBI testing | IGRA generally preferred, TST acceptable | TST remains acceptable when IGRA is unavailable, too costly, or impractical.[1] |
| Healthy children younger than 5 years | TST suggested by ATS/IDSA/CDC; AAP supports IGRA use from age ≥2 years, especially if BCG-vaccinated | Pediatric age cutoffs differ between guidelines.[1][10] |
| High risk of progression, including HIV or major immunosuppression | Either TST or IGRA; consider dual testing when sensitivity is critical | Evidence is insufficient to clearly prefer one test over the other in all high-risk populations.[1] |
| Low-risk person tested despite guidelines and initial test positive | Confirm with a second test, either TST or IGRA | Infection is confirmed only if both tests are positive.[1] |
Two-step TST
[edit | edit source]Two-step TST is used to establish a baseline in persons who will undergo serial TST testing and who have not had a TST within the previous 1-2 years. Remote TB infection, prior BCG vaccination, or nontuberculous mycobacterial exposure may produce waning immune reactivity, so the first TST may boost the immune response and make a later TST appear falsely converted.[1][11]
If the first TST is negative, a second TST is placed 1-3 weeks later. If the second test is negative, the person is considered uninfected at baseline. If the second test is positive, this is interpreted as boosting rather than new infection.[11]
Two-step testing is recommended when TST is used for baseline testing in healthcare personnel, selected residents of congregate facilities, and travelers who will undergo serial TST testing. Two-step testing is unnecessary when using an IGRA.[5][11]
False-positive and false-negative results
[edit | edit source]| Test | False-positive causes | False-negative causes |
|---|---|---|
| TST | Prior BCG vaccination, especially vaccination after infancy or repeated BCG vaccination; infection with nontuberculous mycobacteria; incorrect administration; incorrect interpretation; wrong antigen product. The effect of BCG vaccination given in infancy is usually minimal after 10 years.[1][2] | Recent TB infection within 8-10 weeks; advanced immunosuppression; HIV with low CD4 count; very young age; recent live-virus vaccination such as measles or varicella; overwhelming TB disease; incorrect administration or reading. |
| IGRA | Low pretest probability; rare cross-reactivity with nontuberculous mycobacteria containing ESAT-6 or CFP-10, such as M. kansasii, M. szulgai, or M. marinum. | Advanced immunosuppression; young age; improper specimen handling; delayed incubation; lymphopenia; indeterminate or invalid assay response. |
Borderline or low-positive IGRA results may have limited reproducibility, especially in low-risk populations. When testing is performed despite low pretest probability, confirmatory testing is recommended after an initial positive result.[1]
Screening in special populations
[edit | edit source]Persons with HIV infection
[edit | edit source]All persons with HIV infection should be evaluated for LTBI at the time of HIV diagnosis, regardless of epidemiologic risk.[6] Either TST or IGRA may be used; IGRA is preferred in BCG-vaccinated persons. TST is positive at ≥5 mm in persons with HIV.[6]
Progressive immunodeficiency reduces the sensitivity of both TST and IGRA. Persons with HIV who initially test negative during advanced immunosuppression should be retested after immune reconstitution on antiretroviral therapy if they remain at risk.[6] Annual retesting is recommended for persons with ongoing exposure risk.[6]
In a U.S. prospective study of persons with HIV, T-SPOT.TB had the highest specificity and positive predictive value, whereas QFT-GIT had higher sensitivity than TST. These data support guideline statements that test performance varies with immune status and that no single test is clearly preferred for all persons with HIV.[6]
Children and adolescents
[edit | edit source]Children should be tested only when they have risk factors for TB infection or progression. Testing should not be performed routinely in low-risk children.[10]
The ATS/IDSA/CDC guideline suggests TST rather than IGRA in healthy children younger than 5 years, whereas the American Academy of Pediatrics supports IGRAs in children aged 2 years or older, especially if BCG-vaccinated.[1][10] This creates a practical pediatric cutoff discrepancy: CDC TST interpretation tables use children younger than 4 years in the ≥10 mm threshold group, while AAP guidance often uses younger than 5 years when discussing high-risk pediatric testing considerations.[7][10] In exposed young children, a negative initial test does not exclude recent infection; repeat testing 8-10 weeks after last exposure is required.[10]
Pregnancy
[edit | edit source]TST is not contraindicated during pregnancy. Either TST or IGRA may be used when risk factors for TB infection or progression are present.[7] Screening should not be delayed when the pregnant patient has recent exposure, HIV infection, or other major risk factors for progression.
Healthcare personnel
[edit | edit source]The 2019 National Tuberculosis Controllers Association and CDC recommendations changed the approach to healthcare personnel screening. Baseline screening is still recommended, but routine serial testing is no longer recommended in the absence of known exposure or ongoing transmission.[5]
| Category | 2005 approach | 2019 NTCA/CDC approach |
|---|---|---|
| Baseline preplacement screening | TB screening, symptom evaluation, and TST or IGRA for personnel without documented prior TB disease or LTBI. | Same, with addition of individual TB risk assessment.[5] |
| Postexposure testing | Symptom evaluation for all exposed personnel; test at exposure recognition and repeat 8-10 weeks after last exposure if initially negative. | Unchanged. |
| Routine serial testing | Based on facility risk classification; used in medium-risk settings and settings with ongoing transmission. | Not routinely recommended unless exposure or ongoing transmission occurs; may be considered for selected high-risk groups. |
| Annual requirements | Serial testing in some settings. | Annual TB education for all healthcare personnel. |
| Positive test result | Referral to determine whether LTBI treatment is indicated. | Treatment is encouraged for all healthcare personnel with untreated LTBI unless medically contraindicated. |
If baseline testing is positive in a healthcare worker who is asymptomatic and low risk, a second confirmatory test should be performed before chest radiography and LTBI diagnosis.[5] Healthcare personnel with untreated LTBI should receive annual symptom screening.[5]
HIV screening in TB clinics
[edit | edit source]HIV testing is recommended for all patients with suspected or confirmed TB disease and for persons diagnosed with LTBI or identified as TB contacts. Testing should be offered using an opt-out approach, meaning that testing is performed after the patient is informed unless the patient declines.[12]
Separate written consent and prevention counseling are not required for HIV screening in healthcare settings unless required by local law.[12]
Chest radiography and computer-aided detection in screening programs
[edit | edit source]In low-incidence settings such as the United States, chest radiography is used primarily after a positive TST or IGRA to exclude active pulmonary TB before diagnosing LTBI.[1] A normal chest radiograph and absence of symptoms support LTBI rather than active pulmonary TB; abnormal radiography or TB symptoms require sputum testing for acid-fast bacilli smear, mycobacterial culture, and nucleic acid amplification testing.[1]
In high-burden settings, chest radiography is also used for systematic screening for active pulmonary TB. Computer-aided detection (CAD) software can interpret digital chest radiographs for TB-suggestive abnormalities and has been conditionally recommended by WHO as an alternative to human readers in screening programs, although all positive screens require bacteriologic confirmation.[13]
Recent prospective studies suggest that CAD-based chest radiography may improve screening throughput in high-burden settings, but thresholds, local prevalence, confirmatory testing capacity, and cost-effectiveness must be considered before implementation.[14][15]
Post-screening evaluation
[edit | edit source]A positive TST or IGRA result requires clinical evaluation to exclude active TB disease before LTBI is diagnosed and treated.[1][2]
| Step | Action |
|---|---|
| 1 | Assess for symptoms of active TB, including cough, fever, night sweats, weight loss, hemoptysis, fatigue, and extrapulmonary symptoms. |
| 2 | Obtain chest radiography. |
| 3 | If symptoms are present or chest radiograph is abnormal, evaluate for active TB disease with sputum acid-fast bacilli smear, mycobacterial culture, and nucleic acid amplification testing. |
| 4 | If asymptomatic and chest radiograph is normal, diagnose LTBI and offer treatment after excluding contraindications. |
Common pitfalls
[edit | edit source]- Screening low-risk persons, which increases false-positive results.
- Measuring erythema rather than induration when reading the TST.
- Using a single TST cutoff for all patients rather than risk-stratified thresholds.
- Using TST or IGRA to rule out active TB disease.
- Failing to perform chest radiography after a positive TST or IGRA.
- Treating a positive test as LTBI before excluding active TB disease.
- Ordering routine annual TB testing for all healthcare personnel despite the 2019 NTCA/CDC update.
- Using older QuantiFERON-TB Gold In-Tube language when QuantiFERON-TB Gold Plus is the current-generation assay.
- Using TST or IGRA to monitor response to anti-tuberculosis therapy.
References
[edit | edit source]- ↑ 1.00 1.01 1.02 1.03 1.04 1.05 1.06 1.07 1.08 1.09 1.10 1.11 1.12 1.13 1.14 1.15 1.16 1.17 1.18 1.19 1.20 1.21 1.22 1.23 Lewinsohn DM, Leonard MK, LoBue PA; et al. (2017). "Official American Thoracic Society/Infectious Diseases Society of America/Centers for Disease Control and Prevention Clinical Practice Guidelines: Diagnosis of Tuberculosis in Adults and Children". Clin Infect Dis. 64 (2): e1–e33. doi:10.1093/cid/ciw694. PMID 28100511.
- ↑ 2.0 2.1 2.2 2.3 2.4 2.5 2.6 Shah M, Dorman SE (2021). "Latent Tuberculosis Infection". N Engl J Med. 385 (24): 2271–2280. doi:10.1056/NEJMcp2108501. PMID 34818478 Check
|pmid=value (help). - ↑ 3.0 3.1 3.2 3.3 US Preventive Services Task Force, Mangione CM, Barry MJ; et al. (2023). "Screening for Latent Tuberculosis Infection in Adults: US Preventive Services Task Force Recommendation Statement". JAMA. 329 (17): 1487–1494. doi:10.1001/jama.2023.4899. PMID 37129644 Check
|pmid=value (help). - ↑ 4.0 4.1 "Latent TB Infection Testing and Treatment: Summary of U.S. Recommendations". Centers for Disease Control and Prevention. 2020. Retrieved May 27 2026. Check date values in:
|accessdate=(help) - ↑ 5.0 5.1 5.2 5.3 5.4 5.5 Sosa LE, Njie GJ, Lobato MN; et al. (2019). "Tuberculosis Screening, Testing, and Treatment of U.S. Health Care Personnel: Recommendations From the National Tuberculosis Controllers Association and CDC, 2019". MMWR Morb Mortal Wkly Rep. 68 (19): 439–443. doi:10.15585/mmwr.mm6819a3. PMID 31099768.
- ↑ 6.0 6.1 6.2 6.3 6.4 6.5 "Guidelines for the Prevention and Treatment of Opportunistic Infections in Adults and Adolescents With HIV: Mycobacterium tuberculosis Infection and Disease". National Institutes of Health. 2025. Retrieved May 27 2026. Check date values in:
|accessdate=(help) - ↑ 7.0 7.1 7.2 7.3 7.4 "Tuberculin Skin Testing". Centers for Disease Control and Prevention. 2024. Retrieved May 27 2026. Check date values in:
|accessdate=(help) - ↑ Zhang Y, Zhou G, Shi W; et al. (2023). "Comparing the Diagnostic Performance of QuantiFERON-TB Gold Plus With QFT-GIT, T-SPOT.TB and TST: A Systematic Review and Meta-Analysis". BMC Infect Dis. 23 (1): 40. doi:10.1186/s12879-023-08008-2. PMID 36650462 Check
|pmid=value (help). - ↑ Jonas DE, Riley SR, Lee LC; et al. (2023). "Screening for Latent Tuberculosis Infection in Adults: Updated Evidence Report and Systematic Review for the US Preventive Services Task Force". JAMA. 329 (17): 1495–1509. doi:10.1001/jama.2023.3954. PMID 37129645 Check
|pmid=value (help). - ↑ 10.0 10.1 10.2 10.3 10.4 Nolt D, Starke JR (2021). "Tuberculosis Infection in Children and Adolescents: Testing and Treatment". Pediatrics. 148 (6): e2021054663. doi:10.1542/peds.2021-054663. PMID 34801834 Check
|pmid=value (help). - ↑ 11.0 11.1 11.2 "Tuberculosis". CDC Yellow Book. 2024. Retrieved May 27 2026. Check date values in:
|accessdate=(help) - ↑ 12.0 12.1 "Recommendations for Human Immunodeficiency Virus Screening in Tuberculosis Clinics". Centers for Disease Control and Prevention. 2024. Retrieved May 27 2026. Check date values in:
|accessdate=(help) - ↑ "WHO consolidated guidelines on tuberculosis. Module 2: Screening. Systematic screening for tuberculosis disease". World Health Organization. 2021. Retrieved May 27 2026. Check date values in:
|accessdate=(help) - ↑ Macpherson L, Kik SV, Quartagno M; et al. (2025). "Diagnostic Accuracy of Chest X-Ray Computer-Aided Detection Software for Detection of Prevalent and Incident Tuberculosis in Household Contacts". Clin Infect Dis. 80 (3): 626–636. doi:10.1093/cid/ciae528. PMID 39432010 Check
|pmid=value (help). - ↑ Crowder R, Thangakunam B, Andama A; et al. (2026). "Diagnostic Accuracy of Tuberculosis Screening Tests in a Prospective Multinational Cohort: Chest Radiography With Computer-Aided Detection, Xpert Tuberculosis Host Response, and C-Reactive Protein". Clin Infect Dis. 82 (2): e239–e247. doi:10.1093/cid/ciae549. PMID 39611909 Check
|pmid=value (help).
 EncycloReader
is supported by the
 KSF